Mesalamine for ulcerative colitis is one of those medications that sounds more complicated than it behaves. Its job is refreshingly focused: calm inflammation in the colon and rectum, help mild to moderate ulcerative colitis flares settle down, and keep remission from slipping out the back door wearing sunglasses. For many people with ulcerative colitis, mesalamine is the dependable “first-line” treatment doctors reach for before moving into stronger therapies.
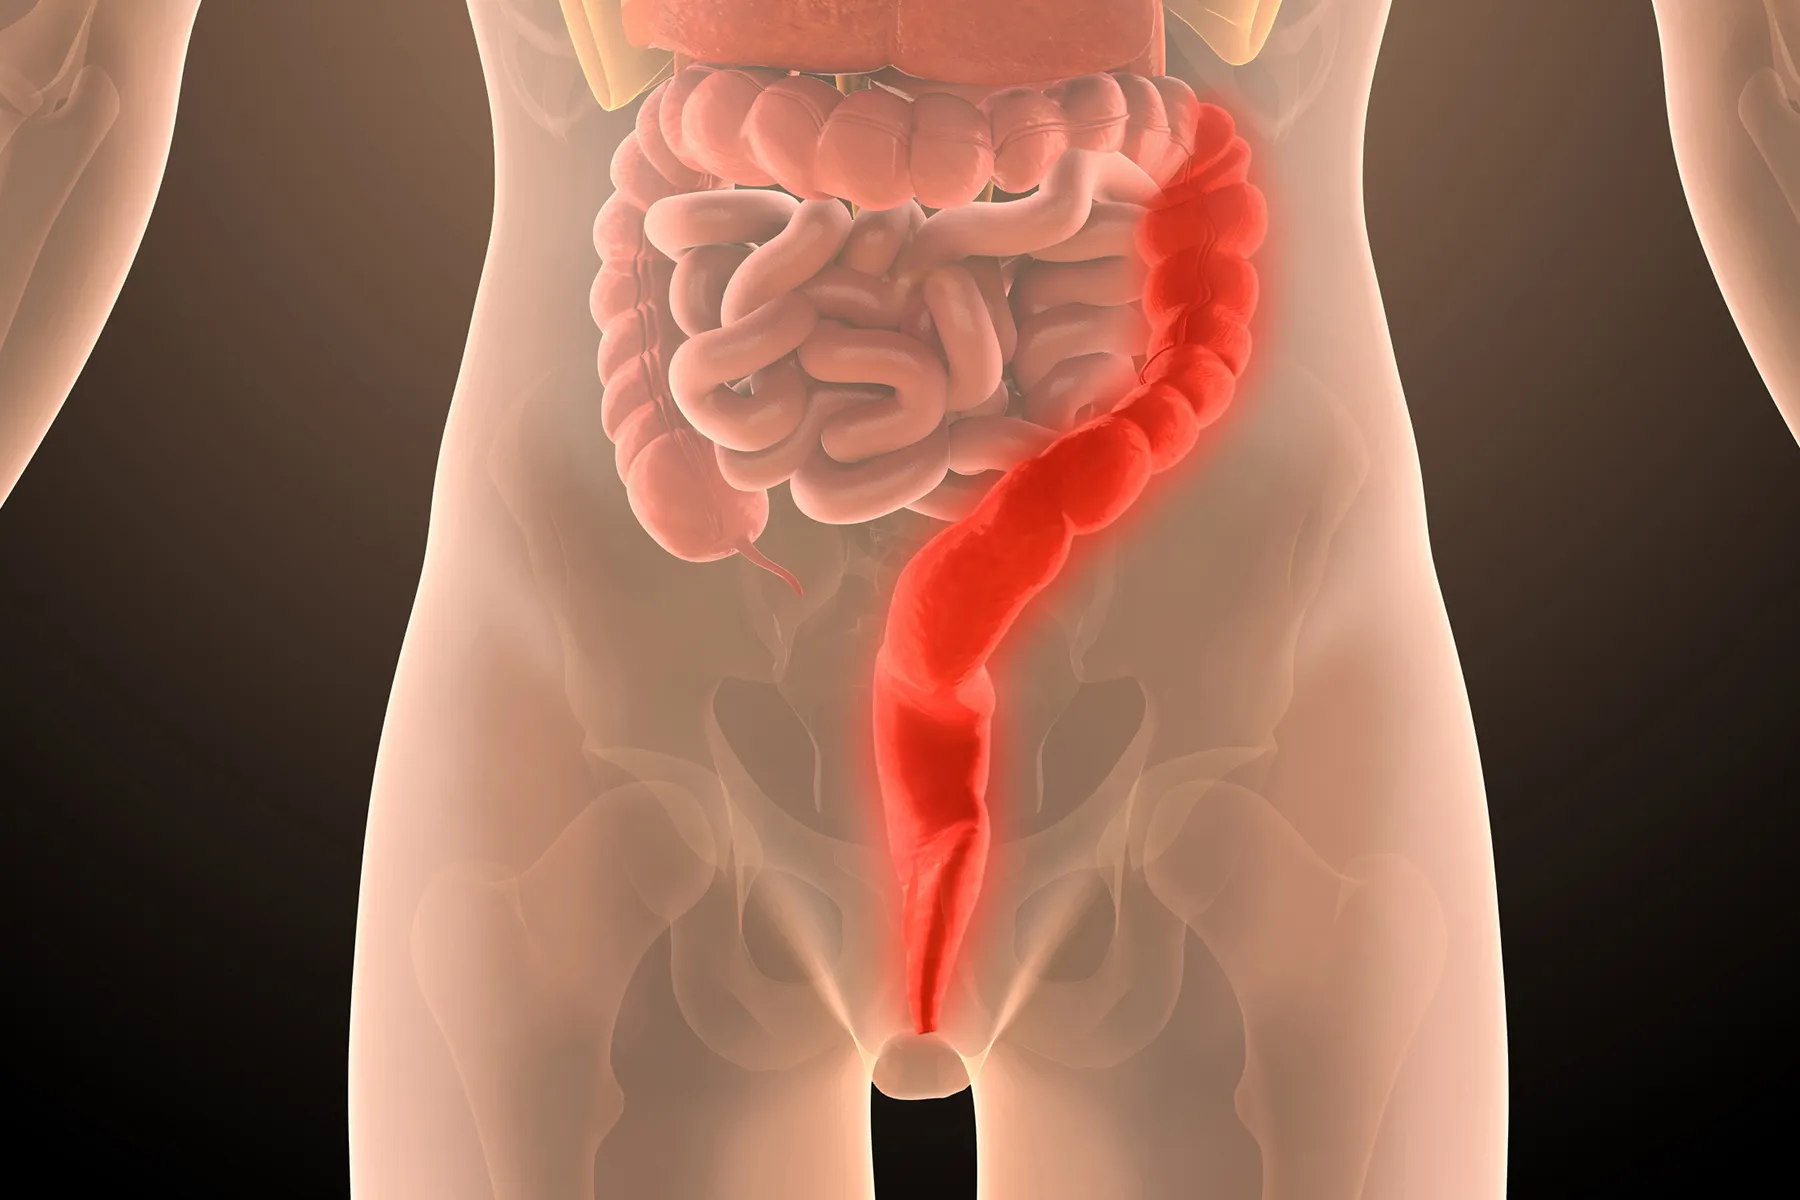
Ulcerative colitis, often shortened to UC, is a chronic inflammatory bowel disease that affects the lining of the large intestine. Symptoms can include bloody diarrhea, urgency, abdominal cramping, fatigue, and the deeply unfair need to know every bathroom location within a five-mile radius. Mesalamine does not cure UC, but it can reduce inflammation, support healing of the intestinal lining, and help many patients stay steady between flares.
This guide explains how mesalamine works, who it may help, the difference between oral and rectal forms, possible side effects, and practical experiences that can make daily treatment easier. Consider it your friendly roadmapminus the medical-school tuition.
What Is Mesalamine?
Mesalamine is an anti-inflammatory medicine in a class called aminosalicylates, also known as 5-ASA medications. It is used mainly for mild to moderate ulcerative colitis, both to treat active symptoms and to maintain remission once symptoms improve.
The active ingredient, 5-aminosalicylic acid, works locally in the intestinal lining. That local action matters. Unlike systemic steroids, which travel widely through the body and can bring a parade of side effects, mesalamine is designed to deliver anti-inflammatory help directly where UC is causing trouble: the colon and rectum.
Mesalamine comes in several forms, including delayed-release tablets, extended-release capsules, granules, enemas, and suppositories. Brand and generic versions may release the medication in different parts of the digestive tract, which is why switching products should be discussed with a clinician instead of treated like swapping one cereal box for another.
How Mesalamine Helps Ulcerative Colitis
Ulcerative colitis inflammation begins in the rectum and can extend upward through part or all of the colon. Mesalamine helps reduce inflammatory activity in the bowel lining. When inflammation decreases, symptoms such as rectal bleeding, diarrhea, mucus, urgency, and cramping may improve.
Induction vs. Maintenance: Two Different Jobs
Mesalamine is commonly used in two phases of UC care:
- Induction of remission: treating an active mild to moderate flare so symptoms calm down.
- Maintenance of remission: continuing treatment after improvement to reduce the chance of relapse.
This distinction is important because some patients feel better and think, “Great, problem solved,” then stop taking the medicine. Unfortunately, UC is not usually impressed by optimism alone. Maintenance therapy is often part of the long game, especially for people who have recurring flares.
Oral Mesalamine vs. Rectal Mesalamine
Mesalamine treatment often depends on where inflammation is located. UC is not a one-size-fits-all condition, and the colon is not exactly a studio apartment. Location matters.
Oral Mesalamine
Oral mesalamine is taken by mouth as tablets, capsules, or granules. It is commonly used when inflammation affects the left side of the colon or extends more broadly. Different oral products are designed to release medication at different points in the intestine, which is one reason dosing instructions vary.
Some oral mesalamine products are taken once daily, while others are taken multiple times per day. Once-daily dosing can be helpful for adherence because, frankly, people have lives, alarms get ignored, and lunch meetings do not pause for perfectly timed medication schedules.
Rectal Mesalamine
Rectal mesalamine comes as suppositories or enemas. Suppositories are commonly used for ulcerative proctitis, where inflammation is limited to the rectum. Enemas can reach farther, often helping inflammation in the rectum and sigmoid colon.
Many patients initially greet rectal therapy with the enthusiasm usually reserved for tax audits. That reaction is understandable. But rectal mesalamine can be very effective because it delivers medication directly to the inflamed area. For left-sided UC or proctosigmoiditis, clinicians often recommend rectal mesalamine alone or in combination with oral mesalamine.
Combination Therapy
For some people, using both oral and rectal mesalamine works better than oral therapy alone. The oral medication supports broader colon coverage, while the rectal form targets the lower colon and rectum, where symptoms such as urgency and bleeding often shout the loudest.
Who May Benefit Most From Mesalamine?
Mesalamine is most often used for people with mild to moderate ulcerative colitis. It may be especially useful for patients with:
- Ulcerative proctitis
- Proctosigmoiditis
- Left-sided ulcerative colitis
- Mild to moderate extensive colitis
- UC symptoms that previously responded well to 5-ASA therapy
Mesalamine is generally not enough for severe ulcerative colitis, serious complications, or flares with high fever, severe dehydration, major bleeding, or signs of toxic megacolon. In those situations, doctors may use corticosteroids, immunomodulators, biologics, small-molecule therapies, hospitalization, or surgery depending on severity.
Common Mesalamine Dosage Patterns
Mesalamine dosage varies by product, form, disease location, age, weight, and whether the goal is flare treatment or remission maintenance. Some adult oral regimens use total daily doses in the range of about 2.4 grams to 4.8 grams for active mild to moderate UC, while maintenance doses may be lower depending on the specific product and clinician recommendation.
Rectal suppositories are often used once daily, commonly at bedtime. Enemas are also frequently used at night so the medication can stay in contact with the colon lining for several hours. This is not glamorous, but neither is running to the bathroom six times before breakfast. Practical wins count.
The most important rule is simple: follow the exact instructions for your prescribed product. Do not crush, chew, split, or switch formulations unless your clinician or pharmacist says it is safe. Many mesalamine tablets and capsules are built with special coatings that control where the medication is released.
How Long Does Mesalamine Take to Work?
Some people notice improvement in bleeding, urgency, or stool frequency within a few weeks. Others need more time, especially if inflammation is more widespread or symptoms have been active for a while. Clinical trials and prescribing information often evaluate treatment over six to eight weeks, but individual timelines vary.
If symptoms are not improving, or if they worsen, it is important to contact a healthcare professional rather than quietly suffering while pretending everything is “probably fine.” Persistent bleeding, nighttime diarrhea, fever, weight loss, severe pain, dizziness, or dehydration deserve prompt medical attention.
Possible Side Effects of Mesalamine
Mesalamine is generally considered well tolerated, but “well tolerated” does not mean “impossible to annoy you.” Common side effects can include headache, nausea, abdominal discomfort, gas, diarrhea, indigestion, and sometimes joint or back pain.
Less common but more serious risks may include kidney problems, pancreatitis, liver issues, allergic reactions, chest pain related to heart inflammation, and a mesalamine intolerance reaction that can look like a UC flare. That intolerance reaction may include worsening abdominal pain, cramping, bloody diarrhea, fever, headache, or rash.
Kidney Monitoring Matters
Because mesalamine can rarely affect kidney function, clinicians often check kidney labs before starting treatment and periodically during therapy. This is one of those boring-sounding safety steps that is actually important. Kidneys prefer not to be surprised.
When to Call a Doctor
Patients should seek medical guidance if they develop symptoms such as severe abdominal pain, worsening bloody diarrhea, fever, rash, trouble breathing, chest pain, yellowing of the skin or eyes, dark urine, unusual fatigue, or decreased urination. These symptoms do not automatically mean something dangerous is happening, but they are worth checking quickly.
Mesalamine Is Not a Steroid or Immunosuppressant
One reason mesalamine is widely used is that it is not a corticosteroid and is not typically classified as an immunosuppressant. Steroids can be powerful short-term tools for UC flares, but they are not ideal for long-term maintenance because of risks such as bone loss, high blood sugar, mood changes, weight gain, cataracts, and infection concerns.
Mesalamine’s role is different. It is more like daily fire prevention than emergency firefighting foam. It may not be strong enough for every flare, but when it works, it can help keep inflammation controlled with a favorable safety profile for many patients.
Tips for Taking Mesalamine Successfully
Build a Routine
Medication adherence is one of the biggest real-world challenges in ulcerative colitis care. Missing doses can increase the risk of symptoms returning. Pairing mesalamine with a consistent habitbrushing teeth, morning coffee, or setting a phone remindercan make treatment feel less like a daily negotiation.
Do Not Stop Just Because You Feel Better
Feeling better is the goal, not the finish line. UC can become active again even after symptoms disappear. Continuing maintenance therapy as prescribed may help keep remission stable.
Talk About Rectal Therapy Honestly
If rectal mesalamine feels awkward, inconvenient, or emotionally exhausting, say so. Doctors have heard it before. A good clinician can help adjust timing, technique, formulation, or expectations. The best medication plan is not only medically sound; it is also realistic enough that a human being can actually follow it.
Track Symptoms
A simple symptom log can help identify patterns. Track stool frequency, bleeding, urgency, nighttime symptoms, missed doses, diet changes, stress, and menstrual cycles if relevant. This information can help your healthcare team decide whether mesalamine is working or whether treatment needs adjustment.
Diet, Lifestyle, and Mesalamine: What Fits Together?
Mesalamine treats inflammation, but lifestyle choices can still affect comfort and flare management. During active symptoms, some people do better with lower-fiber, easy-to-digest foods. During remission, a balanced diet with adequate protein, fluids, and nutrients supports overall health.
No single diet cures ulcerative colitis. Anyone promising that cabbage juice, miracle powders, or a “colon reset smoothie” can replace medical therapy should be approached with caution and possibly a raised eyebrow. Food can influence symptoms, but inflammation needs proper medical monitoring.
Sleep, stress management, exercise, and avoiding smoking are also part of the bigger UC picture. Stress does not cause ulcerative colitis, but it can make symptoms feel worse and make medication routines harder to maintain.
What If Mesalamine Does Not Work?
Mesalamine is helpful for many people, but not everyone responds fully. If symptoms continue despite appropriate dosing and adherence, a clinician may recommend stool testing, blood work, colonoscopy or sigmoidoscopy, dose adjustment, adding rectal therapy, short-term steroids, or moving to advanced therapies.
Modern ulcerative colitis care includes several options beyond mesalamine, such as biologics and targeted oral medications. Needing a stronger medication does not mean anyone failed. It simply means the disease requires a different tool. You would not use a butter knife to fix a leaky roof; medicine works the same way.
Practical Experiences With Mesalamine for Ulcerative Colitis
Many patient experiences with mesalamine begin with uncertainty. A newly diagnosed person may leave the gastroenterologist’s office with a prescription, a pamphlet, and the uneasy feeling that their colon has suddenly become a full-time project manager. The first few weeks often involve learning the medication schedule, figuring out whether to take tablets with food, and waiting to see whether bleeding and urgency improve.
A common experience is gradual improvement rather than an overnight miracle. Someone may notice that bathroom trips drop from eight per day to five, then to three. Blood may become less frequent. Urgency may soften from “emergency sprint” to “reasonable walking pace.” These changes can feel small at first, but for a person with UC, they can mean sleeping through the night, commuting with less anxiety, or eating lunch without scanning the room for exits.
Rectal mesalamine creates its own learning curve. Patients often describe the first enema or suppository as awkward, humbling, or mildly ridiculous. Bedtime use can help because lying down makes retention easier. Keeping the medication nearby, using the bathroom first, and creating a calm routine can reduce frustration. Some people find that once they get past the initial awkwardness, rectal therapy becomes less intimidatingand sometimes surprisingly effective for bleeding and urgency.
Another real-world issue is pill burden. Depending on the product, mesalamine tablets can be large, and some regimens require multiple pills per day. Patients may use pill organizers, phone alarms, medication apps, or visual reminders near the toothbrush. The trick is to make the routine boring. In chronic illness care, boring is underrated. Boring means fewer missed doses, fewer surprises, and fewer dramatic colon plot twists.
Some people also experience anxiety about side effects. That is normal. The practical approach is not to panic-read every forum at 1 a.m., although many have bravely conducted that research mission. Instead, patients can ask their clinician which symptoms should prompt a call, when labs should be checked, and what side effects are common versus rare. Clear expectations make treatment feel less mysterious.
Cost and insurance coverage can also shape the mesalamine experience. Different formulations may have very different prices, even when they contain the same active ingredient. If cost becomes a problem, patients should tell their healthcare team or pharmacist. Generic versions, formulary alternatives, manufacturer programs, or different dosing forms may help. Quietly skipping doses to stretch a prescription can backfire by allowing inflammation to return.
Perhaps the biggest lesson from patient experience is that mesalamine works best as part of a partnership. The medication does its job in the colon, but the patient and care team handle the strategy: monitoring symptoms, checking labs, adjusting formulations, and deciding when treatment needs to change. Ulcerative colitis can be unpredictable, but a consistent plan turns chaos into something more manageable.
Conclusion
Mesalamine for ulcerative colitis remains a major treatment option for mild to moderate UC because it targets inflammation directly in the colon and rectum, can help induce remission, and may help maintain remission over time. Oral forms, rectal forms, or combination therapy may be used depending on where the disease is active. It is generally well tolerated, but it still requires careful use, attention to side effects, and periodic monitoring.
The best mesalamine plan is personalized. Disease location, symptom severity, lifestyle, adherence, cost, and patient comfort all matter. For many people, mesalamine is not a flashy medicationbut when it works, it can be the quiet, steady tool that helps life feel less controlled by ulcerative colitis.
Note: This article is for educational purposes only and should not replace medical advice, diagnosis, or treatment from a licensed healthcare professional.